
Surgery
Real-life HoLEP case number 7: Refractory retention-excellent explanation of early apical dissection
Dr. Fernando Gómez Sancha · ICUA
Dr. Fernando Gómez Sancha · YouTube
Language: English. YouTube audio metadata.
Surgical content for professionals. Contains footage of an operation.
Playback connects to YouTube. Your search query is not sent to the player.
About this video
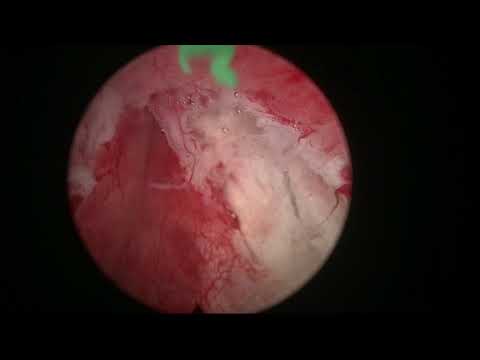
An en-bloc HoLEP for refractory urinary retention using a Lumenis MOSES 120 W laser. The description focuses on releasing the adenoma's apex while protecting the external urinary sphincter and its mucosa. Continence preservation is the teaching objective, without a measured postoperative continence outcome in the written source.
Documented details and sources
Only details explicitly stated in the sources. Missing information does not mean it did not occur.
- En bloc
This video shows an En-bloc HoLEP performed with the MOSES 120 watt laser from Lumenis and it explains how to release the apex of the adenoma from the external urinary sphincter while protecting the sphincter and its mucosa, to allow for excellent postoperative urinary continence.
- MOSES / MoLEP
This video shows an En-bloc HoLEP performed with the MOSES 120 watt laser from Lumenis and it explains how to release the apex of the adenoma from the external urinary sphincter while protecting the sphincter and its mucosa, to allow for excellent postoperative urinary continence.
- Early apical release
Real-life HoLEP case number 7: Refractory retention-excellent explanation of early apical dissection
- Urinary retention
Real-life HoLEP case number 7: Refractory retention-excellent explanation of early apical dissection
Source checked: 2026-10-06.
Available transcript · English
Automatic YouTube captions, not clinically reviewed. Names, technical terms and numbers may contain errors.
They may contain transcription or translation errors; check the explanation in the video.
- swing from her we get some Italian oceans Palestine this particular one will ambient Aquino funnel ocean system was still experimental and in tequila from the usual estaba is Nani mandalas videos you know like in our sister party we have lost okay so now we have this man who was in a urinary retention he had a previous episode some years ago and he when did your attention again and a few times they try to take the catheter out you can see that this is a catheter edema is caused by the tip of the catheter you had a negative urine culture and we're going to perform a Moses a nucleation so we're going to come out to the ethics and study you're not only of this thinking you can see the contour so I'm going to choose
- to mark you seal the limits between the ethics on the center you see it's the limit and bring it down towards the very Montanan also bring it up all the way taking into account of the sting Jake's taking forward you know the interior part is more proximal than the lower part so our incision should follow the limiting distinctly on the ethics now it should it come a little bit more proximal as we go on tear so as we go up we should go in as well that's the idea this is a four or five hours so the top of all fibers this is a very Montana that's the sphincter huh see the prostatic shape varies a lot from one patient to the next and you have to adapt your incisions if you do them to proximal there's still a chance that the
- Mercosur will break when you dissect the plane we get right in the interface right in the edge we'd say of the sphincter and the normal then it will be okay so you see I'm cutting the attachments that unite this winter with the apical prospects in the dorsal area so from from 6:00 to 9:00 69 and from 3:00 to 6:00 and then of course you have good enough disability you can prolong this a little bit coming up the objective of this is not to look for the proper plane still but to generate these moves you see there is a groove between these things on the prostate and that is going to be a very solid landmark to protect the sphincter very solid landmark Tecna stinker and then we are so we're going to push a
- little bit near the very so this is very Montana why we put the tip of the spoke here and do a little bit of natural dissection I mean of pushing forward to the tip of the scope to find the proper plane you see here there's no stress for the sphincter because we are pushing a little bit natural but we have already generated in space so we won't be breaking the distinct er the lower part if we do our limited natural motion to define the plane now we also going to cut now to the mostess fiber join one thing with the other here we are joining the two sides into one single force to your plane now once there is a small chamber here where I can put the scope in the fiber I will keep the fiber as 12 o'clock for the
- rest of it you see here and I will establish the line of attack the line of dissection is clearly that this plane to serve as a guide you see sometimes we don't see exactly I mean distinguishing the plane is a little bit esoteric in the sense that of course here for example you can tell that we are in a good plane but not always throughout the procedure you can tell exactly that you are in the good plane sometimes the tissue quality is a little bit different but having the line of attack or the line of dissection as a uniform curved line you know this is a smiling that's a line helps us a lot because you might be not exactly in the proper plane but you're going to be very close to that plane if you follow this
- line of that section normally the mechanical is a shock waves that the humming produces will open the plane for you so you have to point at a certain distance of the tissue that gives you a nice the disruption of the fibers that are joining the capstone with the adenoma and at the same time you have to make sure that it provides reasonably good enough stars if you see this plane is very beautiful so this is a good thing because we have a good it's an example of a good plane and then as I said if you follow this line of that section even when the plane is maybe not so clear here sometimes you can do a little bit of mechanical excursion but I rather don't do a lot of mechanical dissection because there's usually no
- need only when you are in doubt you know and you can do a little bit of pushing with the tip of the spoke to see we are in the proper plane but the concept of this line of attack is quite good because you see it allows you to dissect a very uniform name here you can see the posterior aspect of the sphincter has already been released now to go until your knee I'm going to cut initially on the prostate you see on the prostate why because this is a sphincter so if I cut following this plane what I'm going to do is release it from the effects of the prostate here we are reaching well pop off here the incision is more horizontal but now what happens when you go in you see we have gained a lot of access this
- is the line I cut thanks to that I can see now the proper plane much better and I have better access I think this is a very paramount concept to incise the ethics a little bit to release it from the apex and then it's very easy to find the proper plane and also as we come up with the scope you see many techniques show you how lateral load is I said that upwards but nobody looks back to this thing to check what's going on and you know I try to look back and do four incisions you see on the prostate so we get better access to the to the plane it's the and this way what you do is the chief to protect the Slinker completely I mean you're cheap to protect the mucosal distinction which is I think very relevant for a proper immediate
- post-operative marinara countenance and this is 12 o´clock fibers here the series is the limit of a swing for this optical tissue here I'm cutting towards the 12 up of five hours you are it's interesting that we find these fibers when we enter let's say the until your plane and we will find all the vertical fibers when we exit we until your plane and enter the latter so until nearly you have to look for the vertical fibers at 12 o´clock to enter the interior plane cut also to exit airplane and enter the latter ok on the other side we will do the same you see here you can see there's some attachments of the extincter and the ethics I'm going to do a cut on the tissue you know just to release the
- article tissue a little bit from there from the thinker and to generate some some space so when I go in I can look for the or the right plane you see here and I can try to follow the the right plane and by generating that let's say space I can put my scope in there like and follow the plane very very carefully coming towards the interior see here I have to protect the sphincter also in this area so here I'm going to cut horizontally into the prostate I don't mind this in the right plane or not but I am taking the the battlefield a little bit more inside towards the sphincter 12 o'clock now of course I will go back to check the good plane you see here of course you have better access to develop
- this plane and we know that the sphincter lies a little bit behind so it's less chances of damaging let's go let's proceed with this plane and this dissection I'm going to go a little bit deeper let's say in here so I can bring it up bring it up bring it up move it up here the tissue is obstructing my view that I know that I'm in a good position I'm doing a good thing here and we to drop off again and I'm reaching the 12 of the pirate again you see we can recognize this there if you leave easily here we are this is a section of the Interior plane I want to go now Asante VRS I'll come because the sphincter is lying they find us already I don't want to leave any interior tissue hanging from the sphincter that
- could lead to obstruction at some stage here you see we can come back to the proper plane on the other side develop it a little bit further and take plane all the way until early until I am able to connect let's say with the other side here to keep it for example if you suspect you're close to its Internet in a certain point but we are reaching the interior plane that we live from the other side so now we have managed to release the sphincter completely on where we are so again coming up coming up coming up if you follow this direction of the fibers of the cut song that are telling you where to go it's an optical future this is the connection with the plane on the on the other side initially the space is quite limited you
- see we have to let say struggle a little bit at the beginning but I have to say after this initial say five or six minutes or ten minutes whatever it takes you have a very nice circumferential playing at that section the water is going to irrigate this it's a space which is small at the beginning but we'll get the rest of the larger and as we develop more and more display alright so see having this line of attack allows you to continue with your dissection and then the only worry is to go let's say to deepen the capsule so we're going to make a dissection that is quite gentle so it allows us to judge if we are in the right plane or maybe too deep if we are too deep you see for example here you could tell I'm going a very
- deep very deep so just get a little bit more media with your fiber and correct to see the dissection plane doing say violating the the peripheral zone it's not a problem unless you continue with this capture of violation and you perforated so you have to stop before a profession happens that's usually relatively easy if you let's say progress slowly and carefully you'll see that even when we progress ranking it slowly this is alright faster technique then we are accepting the plane and clearly checking the carcass of the tissue trying to follow the curve you know we're not dissecting straight lines with expecting a circumferential plane so as I progress I get closer to the to the adenoma let's go to the other side and
- see how this is now progressing you sleep here it's like a good plane and try to follow the line that might be a little bit deep so I want to correct here and you see it's not a big deal you know the fiber measures only half a millimeter so leaving one millimeter more or less of tissue it's not really relevant when we look at the big picture we are removing 80 90 percent of the anomalous sorry of the total volume of the prostate so first we don't want to leave bulk the amount of normal tissue and we don't want to leave any nodule you know any an anomalous module but this - minimal irregularities from the from the capsule are not important so this focus on the big picture you know follow your line of attack here you
- haven't established a proper that's me aunt in your plane I'm going to try to establish the better plane so we can let's say put the scope on there nama a lower a little bit lower the Anoma and have a better visibility here of course I don't want to go let's say too long I'm going to try to stay up stay up see maybe remove the enormous tissue that will be sticking to the interior part but I said trying to establish a interior plane it's not nobody's in there was a remnant of tissue layer but I corrected the plane to take it out that looks a little bit deep so we will stay somewhat low lower you see it's a matter of judging first trying to recognize the proper plane but when when it's not evident just following the
- curvature of the prostate and Chowchilla going to D o at the end of the procedure we will be able to judge if you left any significant amount of tissue and there's a number of ways to do that you have to look at the shape of the cavity you have to see that there is no bumping you know remaining tissue there and also you can use post-operative or interpretive office on transrectal ultrasound as we do sometimes to check the quality of the fossa usually despite having a relatively regular the static surface when we do ultrasound you realize that it was very anatomic and we were able to reach the proper plane and the proper depth there is no significant amount of tissue remaining see we have to find a
- way to simplify Halep so what everybody can learn it I think was in a Congress in the National Congress in Spain and there is the German speaker discussing politics said this is only for very talented surgeons on if you are over 50 forget about it because you will not be able to learn it and I think what's a very discouraging statement I think of course we know technique is very demanding because you need very good orientation and starting to do the cleanup that this might be a little difficult this technically means challenging aspect with the article liberation but it's not so difficult to learn it's very very let's say structure very and it's a very reproducible and I have been teaching it to a lot of people
- and they are able to do it now extremely happy with their and block operation from here you see this is the bladder neck up here and here we are at the 12 area entering the bladder alright I'm not going to do to push it through for the moment I'm going to try to make a really better dissection because the moment we enter the bladder we will lose let's say this excellent irrigation that provides us with excellent visibility and I'm going to try to progress a little bit more in the lower aspect and the next thing the lower aspect we decides lateral aspects before we enter the ladder and then everything will be blazingly fast when we open the bladder neck we will be able to cut through the bladder neck
- circumferentially I mean very fast we will finish the procedures you see all it with is a block approach and with this technology so there's there's been advances not only in technique the disturbing on technique but also in technology we can get very very consistent helped us is very consistent analysis so here yeah that might look like an audio now we have to check sometimes you can check if you're going to be leaving tissue behind just by going carefully huh course if we see that the capsule gets very thin you might say refrain from doing this but I think it was maybe a smaller number of tissue layer sometimes the the fiber plastic Lucy gets a little bit fat from the fiber and a little bit irregular and it becomes a
- lil bit uncomfortable that happens you can get a pair of scissors and just cut the end of fibrin and continue the procedure I'm a little bit impatient I always want to finish as early as possible sometimes I struggle with this green Klingons alright so there we are you see this is natural try to follow that plane here you follow this plane we're going to get towards the interior part much we must be nearing the bladder neck what's on tissue I'd like to remove as well there's nothing wrong you see the same way when we were entering the capsule a little bit we corrected we can correct we'll go back and take a little bit more tissue out if you think that it's worth it sometimes it's difficult to say this
- is going to be an ordeal or what yeah that's getting deeper we're getting towards the bladder neck and I think maybe maybe it's due some more pasta here at section let's see how this is coming here it's unlike this a little bit better as we get more and more confident to follow up you realize that oh nothing happens it's very safe for sleeping when you get even a little bit close to the cash flow sometimes when you remove these modules and capsule looks a little bit thin but usually it has no consequence so in many cases you realize how to save this procedure is and we don't tend to panic when you see a little bit of capture or a little bit of fat or a small preparation just you know relax course
- you have to recognize when something happens that it's important but I'm trying to say is that your first reaction is the whole experiment can be anything every time you open a little bit the capsule many times we do that with open prostatectomy many times we do that with trp you know although I haven't done a TRP or opposed to take me for many years but I remember that sometimes you could see a capsule preparation of course the reaction was a little bit panicky because you could open sinuses there was a lot of bleeding situation was not I mean you were using we were using at the time not silent but glycine or shrugged it off it was a little bit more dangerous but now we are using irrigation of salad and we're
- using a relatively low pressure to do this dissection we are using a laser that provides very good tennis classes so it's pretty safe and peaceful operation of course having things that we missed completely and having nice things and I will show you in very good shape you see we respected the sphincter and the mucosa on this thing for and quite relaxed that the patient will not have incontinence and we avoided that possibility from the very beginning of the procedure I can continue my dissection on very happy and very relaxed there's nothing tremendous about Holland you know it's it's a pleasant operation it's very enough for my car and then I have to tell you patients are extremely happy when you go to see the families
- the irrigation is not full of blood it's usually clear or pinky the nurses in the in the words like this procedure because they're not suffering like they were before when they had to irrigate patients after PRP so really I think these procedures is amazing you can treat a very old patient very weak patients now we're going in the bladder okay I'm refraining the mucosa with my with my fiber now I'm cutting the latter neck you see following the curve of the bladder neck letting the energy do its job of cutting you can see that mostly styling enhance has enhanced the cutting properties of omean so [ __ ] fibers sometimes to committee while returning and now you can see that the cutting properties are greatly enhanced iron and
- the mostess technology so great idea this moses pulse modulation that has improved homeostasis has improved the reach of the laser in the sense that it opens the plane very beautifully he also provides excellent how much passes at the same time we can concentrate on the dissection aspect you can concentrate on the plane you can concentrate on the strategy and you don't have to think about controlling the bleeding you know so much because it's usually controlled as you go so here we are this is a fifteen-year aspect we're going around the prostate I'm getting my fiber very close to the tissues so it doesn't disrupt the capsule but just no cuts the attachments in the capsule on the earth Norma and provides
- excellent formulation but there's no capsular that's the violation or or damage here we are you have to learn to navigate the this this cavity this is a circumferential cavity I tell my patients it's like an orange the frost is like an orange we are dissecting we're peeling off the meat of the orange from the skin of the orange and once we finish we will take em it push it into the batter or modulated there we are this is still your aspect this is bladder neck so you see how we managed to reach very close here and I'm going to stop at 6 o'clock I don't want to cross over to the other side from this side and we're going to check how is this bladder neck looking it's much less developed the right time
- at 12 o'clock I'm going to follow the curve at the bladder neck to dissect it let's say towards the linear aspect you see everything is a certain pressure up here you got a neck also and I'm going to cut the lotta neck following this circumference if I did I need a bloody neck incision here the tissue I wanted to take out it's probably some little attachment here see if I can connect this little plane here with another area I think I have to follow this direction to get to that yeah to get closer to the bottleneck you see we are in sizing still bladder neck and separating the Anoma from the capsule there we are then we are check the you oh there it is so now you see we have the sphincter perfect stinko
- we have the adenoma I'm going to push it into the bladder if I can so that I have to lift the lobe and push it this video anytime you can push one go first and then the other lobe will go is here that she's here but here there's still some attachment it is preventing me from seeing completely but you can see we have bladder neck up here up here let's detach this a little bit and keep coming much easier and then we have bladder neck here so I'm going to cut the tissue here maybe progressively to make sure that we can send Norma into the ladder in one piece let's end block the main advantage of this procedure I think is the early optical liberation and the quality of disability the fact that we are
- dissecting a very circumferential playing this is Rachel five only this is not the glandular it's up there so let's continue in this direction connecting the plane as we always feel we want to make a very big corporation if we make a small one it's not a big deal then we are are cutting in the FASTA from the lateral aspect to the midline and at the end of the nucleation face I think there we go I'm going to check a little bit mustaches you see that we lost the laminar flow that was giving us excellent visibility here you see where we're going a little bit deep up there that's not not perfect so I'm going to remove let's say this hanging hanging bits if I can but we don't want to insist flow in different like that
- let's take here and I see this kind of it's a thin thin cup so like that what we have here not very concerned I'm just checking on the status removing any additional piece of tissue we went a little bit deeper than usual and that's because you see the capsule and here is very thin also but here it's holding anywhere I can this is our culture just a little bit mean seer there and no big deal I will remove the catheter tomorrow as well I don't tend to keep the catheter for longer even if we do a little bit of filling thinning of the capsule no leader hard to tell if this is not fishing I'll take it out just in case so this is what I call the trimming place where you check on the status and you check if something it's
- remaining that's why I don't care so much well if if you let's say if you if you leave a lot of a little bit of tissue only belonging to the latter leg that's what I'm saying it's if you have to correct your plane don't worry if you anything that you want something with too much inside because we can check at the end because any remaining leakage which is an experiment then we are so it was a very fast operation you have a pretty good handle passes and went to check this matter neck leather neck area that's also a little bit in the limit it's companies money somebody need Mario Buda look at control beautiful oh okay value a little bit on that he Romero Oh be done you know we're not simple animals if you never played sorry for
- the interruption always being asked if you have another operating room available for they were asking me if we can sleep to get another pitch was ready for the next receiver here we are ah sinker pasta very nice there's some areas where we are near the near the limit of nothing very serious if there is starvation is going to be very little surely non-musical we take the cata car tomorrow morning okay let's mostly going to change my camera connect it to the nephew scope change the light table my nurse is going to take out the endoscope I'm going to help her she's going to pull and then I'm going to go in very fast so I don't decompress the bladder now my water internal turn put it commercial my water flow is a really
- it's open steam because you want some some water coming out and I will compensate yeah that's the bladder neck you see here I am going to lift a little with my hands so I can keep blades away from the bladder wall that's an oscillation face the random oscillator is an amazing tool and provides excellent modulation very fast modulation and allows us to perform these procedures in a very limited time so well it is no longer or doesn't need to be no longer does need to be not correct yeah we have water I'm saying is the toilet tissue or this Bionic I mean the first what's the thing it's confused because I came into the faucet now what I'm saying is that well it doesn't have to be very lengthy procedure full of stress and it's just
- routine procedure I don't tell my patients that they have a significant risk of continuous because they don't have I don't teach them capital exercises before the operation because they usually don't need them so I think we block technique with earlier because released its offering excellent posture very continence rates and it's very low incidence of positive relative stress incontinence it is true that removing the whole and Norma has a lot of benefits long term durability excellent the obstruction excellent chance of recovering the bladder if it's a hydration bladder but there's also some drawbacks some patients tell you you know I don't wear a pad if I am going to pass gas I'm going to fart sometimes I'm not careful
- when I relax the anal sphincter I can feel as if drachmas coming out for ya drop comes out because relaxation of the pelvic floor and the anal sphincter relaxes the external things as well but when you ask them overall push me very happy so we finished the modulation that's the sphincter there we go thank you