
Surgery
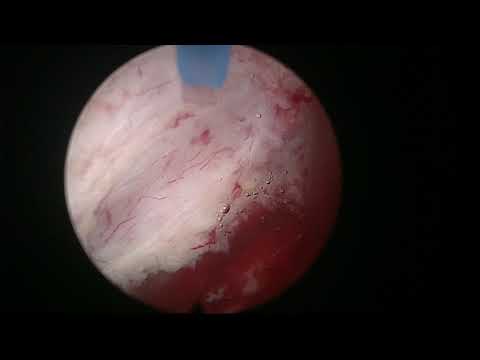
Real life HoLEP case number 13: A bulky prostate with a tendency to bleed more than usual
Dr. Fernando Gómez Sancha · ICUA
Dr. Fernando Gómez Sancha · YouTube
Language: English. YouTube audio metadata.
Surgical content for professionals. Contains footage of an operation.
Playback connects to YouTube. Your search query is not sent to the player.
About this video
A HoLEP case in a bulky prostate with more bleeding than usual, as stated in the title. The description focuses on progressing despite periods of reduced visibility. It does not provide blood-loss measurements or postoperative outcomes.
Documented details and sources
Only details explicitly stated in the sources. Missing information does not mean it did not occur.
- Documented bleeding
Real life HoLEP case number 13: A bulky prostate with a tendency to bleed more than usual
Source checked: 2026-10-06.
Available transcript · English
Automatic YouTube captions, not clinically reviewed. Names, technical terms and numbers may contain errors. Check them against the video; complete audio coverage has not been verified.
They may contain transcription or translation errors; check the explanation in the video.
- okay so this is the last piece of today I think maybe it is a little bit tight but no it's good yeah we have big urethras in Spain maybe so this is the sphincter edge more or less and you can tell this was supposed to be a very large gland maybe it's very wide it's not too long you also are close to the edge we have to be careful later on a little bit to
- regulate it no but this is a very standard very commonly indications we operate snow so let's put the fiber in that's the variable again from here you can see the edge of this finger now here I'm going to mark here the white line so I'm going to try to develop this this white line there is some mucosal bleeding it's quite common so sometimes you can even have trouble let's say finishing the landmark marking of the along the white lines there's a little there's a lot of lot like now where you know it comes to a point where you don't see very well my advice is to go in the
- plane now to look for the plane and start a new cleaning if on the contrary you can you can see very well my advice is to develop let's say a groove you see following the white line if you deepen the white line a little bit you can you can develop a groove that establishes a separation between the adenoma and the apex now let's go into the plane so this is very Montana here you see if you push a little bit with your scope you're going to enter the proper plane very easily Lenny cups and qui relate here I want to release the attachments of the sphincter to the Anoma from 6 o'clock to tonight oh [ __ ] in this side and then on
- the other side I'd like to do the same it's following the white line the typical maneuver to to enter the the proper plane is to put the scope very close in close proximity to the very one tunnel and then push a little bit sideways lateral but you can you can do a little bit of mechanical dissection on the apex that will give you the clue of where is the where is the where is the good plane of course when you have localize the plane in both sides it's only logical to try to connect them in the midline so you cut on top of the very Montana the beginning of the operation sometimes you can have bad visibility but this will very soon
- change let's we will see of course you can try to spend a little time trying to find out where is the bleeding coming from and try to do something low status but most of the times you can just progress and image doesn't really take glades also a lot of the bleeding is coming from the area Noma and as you say we touch the adenoma from the capsule you are sectioning the vessels that yeah so that's the posterior plane I'm going to put the fiber at 12 o´clock I'm going to follow the dissection a little bit further of course if the
- bleeding continues I will try to do something most assets before progressing here you can see that I'm developing the lower posterior plane trying to split the screen into trying to keep the line of attack the line of dissection in the middle of the screen and at the beginning of the procedure my let's say a and is going to be too late to lace against the line here for example see the cuff she was getting a little bit thin here we will have to get say closer to the Anoma but I think this this is probably enough posterior dissection for the moment see where the bleeding is coming from let's see if we can stop it a little bit it's a little bit of a
- nuisance no it's really that we call a people bleeding okay this is vessel there it's maybe you can control that one there's a number of them it's going to be a little bit bloody anyway this is 12 o'clock this is the white line we marked so the next this is the mo person of this thing - you see so the next step is going to be to cut on the prostate try to defend let's say the the white line for we four millimeters five millimeters something like that I'm not trying to develop the plane just I'm trying to cut yeah the adherence is of the ethics to this winter and then I'm going to try to look for the good plan huh
- it's looked like a it of this shoe that was it's a little bit uncomfortable you don't have very good visibility for the moment you get better now let's see if we can we can follow them nice plane let me get some better hostesses where we are trying to come up and looks like a Noma
- trying to go from naturally around the epics here if you come out to see yeah yeah it's clear that we have to cut again a little bit on the prostate horizontally below the sphincter to get to the let's say 12 about five words here this way we we need the sphincter behind us now we can try to say conquer the peaky Oh Vienna Noma 12 o'clock progressively coming up coming up coming up but after having released the
- distinct from the epics and the more most pistol part this is again little bit of tissue of the apex coming towards 12 of
- see here is maybe in a case like this maybe with mosses we would have the same initial bleeding but maybe the control of a moustache this would be a little bit better or easier no just doing the same work and doing the same steps you know coming up I try to look at the direction on the fibers here you see because that gives you the clue or where the plane is going sometimes we decide what to do based on tiny anatomical details you know that you have to be searching for and looking
- for for to develop this understanding of the anatomy with some experience there we are so for the moment we released a big part of the Nova coming towards 12 o'clock this is 12 fibres maybe we can completes the cut here the miscibility it's not so good okay The Watchmen is not particularly low so we have this apical bleeders okay so this is fainter this is the white line we marked and again I'm going to cut on the tissue a little bit on the prostate
- here we are following a good good a good cut then now we look for the good play now this is a good plane when we gain a lot of access by doing that incision on the prostate we are see why I find it useful to develop the posterior plane a little bit because when you're doing this dissection of the lateral aspect you get orientation in the in the lower part in the posterior here we coming up up up you see when you are here you see this is to be okay
- no the disability here is falling very fast let's try to develop this lateral plane a little bit further this allows the tip of their I mean no Matt you follow down you know it comes down you know my scope can go here we are lowering the tip you see so these fibers that sometimes I'll admit parallel to the to the laser fiber become vertical ICC because I'm pushing their nose or the tip of their of the adenoma down you see all these fibers become more accessible now you can cut them just because I position my spoke on this lateral aspect you know trying to push down the other noma let's see we can
- cross over towards the other side let's come out check it yeah it looks like a great plane and now we have connected huh we finally release the effects completely we're in a good plane we can continue our dissection now sir compression there we are
- that's very good now wait connecting see this is a normal let's say a view of the capsule some people say and interiorly there's no wood plane but I disagree I think sometimes we find beautiful plane anteriorly as well you see I'm going to try to of course you have to find speed of dissection that provides you nice developing on the off the plane but on the same time nice and discusses you know if you rush too much you can find that there are many bleeding's going on at the same time and then it might be difficult to establish channel status
- properly no it will take more time you will regret that you did the dissection very fast sometimes you get carried away with how good the plane is and how the dissection is progressing but then of course you leave too many vessels small vessels but too many at the same time you know so it's important to let's say carry a good kind of status as you go and recheck it because many times there is some degree of spasm of the vessels you know when you cut through them and initially they don't bleed but then they start bleeding a little bit so of course we don't want to go too slow you know
- generating very very exaggerated hemostasis snow and widening of the whole fossa you know it's not usually necessary so you have to try to find the right balance no for you of speed of dissection and quality thinnest assets but in general you see now we got excellent visibility now we have very good visibility and that's because we are irrigating a very small space you know just the space between the Anoma and the capsule that allows us to see very well leave this tiny blob in the
- irrigation fluid will clear it just being a bit careful with the hostesses usually you can progress reasonably fast also you can see that I'm not lifting the pen off my foot from the fellow I am dissecting let's say continuously continuously all the time just very brief stops what I have to check something and I have to come back check stuff but that makes this operation extremely fast you see and that's progressing stopping regulate not too much not too little just enough let's say here
- you see the the fact that we are dissecting a circumferential plane makes it very easy to be recognized and in in between some area you're not totally sure of maybe you've seen this and you think is this a good plane okay let's go up a little bit let's go down a little bit you see this is going to give you some orientation so of course if it becomes I'd say if it looks deep or if it looks as if you're getting deeper and deeper you can correct you see by getting closer to the odd number and then you leave we see a little bit of here is where we change no we were following this plane it looked a little bit leap so I changed the direction of the fiber to correct the plane again
- force us as we passed the equator again of the dissection the fiber has to point a little bit closer to the earth normal not not right that's the line of attack as we were doing at the beginning this is because of the you know spherical nature of the anomaly we have to initially the plane was looking up going up now the plane has to go down here initially it was going outside and now it has to go let's say inside you know to the midline so instead of firing right at the line of attack which can go I mean I can go in the castle like that you know you have to get progressively closer closer closer to the a number stay close because if you stay close to
- their normal what will happen is that the fibers that are touching the normal to the capsule will be capped by the energy but there will be very little energy going into the capsule and some leaders it's a plexus no more than anything let's leave we can follow the right lane there and get to the bottom the base about Lexus follow the plane here you see here we see circular fibers again is the bladder neck here we see vertical fibers this is the entrance to the bladder now we open some vessel which is leaning on our face did you see that everything gets red you
- shouldn't be afraid most likely there is a vessel single vessel bleeding on your on your face you know what I mean so it doesn't mean that the patient's bleeding too much or anything just sometimes if you get some distance you can see where the bleeding is coming from uncontrolled it's a little bit better but let's open the bladder neck a little bit more we don't want a lot of vessels bleeding at the same time but I think if we open the better neck we will be able to see where are these vessels and this is all platypus I see
- it's bladder it's again you always were close yes but as we are now in the interior aspect for the moment we don't worry about that one and we'll have to check as we cut let's say the bladder neck towards towards the posterior area huh here what I'm doing is trying to correlate you know those vessels that we're getting from the mucosa so if we develop the bladder neck a little bit more and we cut the bladder neck we will have to look and inside and see where the uoz are that's a good suggestion it
- tells me that you're understanding the procedure very well initially it's a little bit strange to see these apical liberation but more cases we see the more you understand it and the more you are able to predict you know what I'm going to do next it means that you understand the procedure is very important to watch cases before you try to do it on your own because and of course if you can have a mentor we do it's it's much much better we were discussing before that if you're going to start your own experience it's very important to select the cases properly initially you see that I'm dissecting the plane very very fast initially you're going to be very slow you're
- going to go like that very carefully you know very very slow so if you do a very large gland it might get very tedious and very lengthy and so my advice is to choose prostates but are bigger than 40 grams maybe 50 60 70 also if you're going to start on your own not idealize it's much better always to have the same mentor can help you take you out of trouble and let's say it's you just being by your side you know the idea is you're
- starting on your own that you can always resort to the receptor scope in case of trouble do you all it's very very close and of course if you want to handle let's say a prostate in this state know where some of the prostate has been detached from the adenoma some of the processes are touched with our sexy scope it's not an easy section so I would choose to do that on a very large gland but if it's a 60 gram prostate maybe you you can perfectly get out of trouble you know finish the case and
- also I think very often we try to when you are doing something new we try to oversell it to the patient's you know especially especially when when they only had to pay for it now let's say if it's something that their insurance doesn't cover or something them so I think it's a bad idea I think it's better much better to tell the patient this is let's say probably safer but you know in some instances we might need to convert the qrp my goal is going to be that you are going to be relieved of your symptoms there's any trouble I will stop and that's a very clear recommendation as well if you have any
- trouble that you cannot deal with it's always better to stop patients are never unhappy with you tell them I stopped because it was not safe to continue so this happened to me a couple of times during my learning curve and I told the patient I stopped we couldn't finish the procedure what's not safe and I thought what would I do with you know a family member huh you want safety first so it's always safer to come back another day with things I have settled many times if you leave a prostate let's say like this imagine that you cannot finish whether it's a perforation or something and we decide to stop coming back and orienting yourself after some days it's much easier if there was a
- perforation it has already closed then you can each easily finish the procedure so at the beginning of your experience maybe you can tell the patient there's a small chance that we will need to go to stage but I think that despite let's say common understanding no all up is not so difficult to learn I think TRP is a much more difficult we have all learned your Pino despite well I haven't done one for many many years I haven't done a tea or
- people I don't know since 2003 I think 17 years course I'm doing a much better job now than I was doing at the beginning when I was using the green highlighter for vaporization but so that's the posterior plane what's the the bladder neck you see so you need to continue I'm going to be very careful here trying to continue close to the adenoma see close to the anterior aspect close to the elenova
- like that see if you went this way it would be a problem but as long as you stay you know close to the adenoma and see that we are respecting that layer that's all there might be a little bit thin
- you see when they come to this side you see that's to get close with close get close no it doesn't matter if you leave a little bit of tissue there because that's actually the castle what you living you know
- remember to try to do let's say relatively wide movements because if you go a little bit fast you know the the fastness the speed of dissection you know provides a very nice detachment of their Noma but also very safe you see that you can find a working distance that produces this effect of opening the plane and giving you some kind of status of the remaining tissue you have to be thinking one suddenly know many people are a little bit like robots when happened with the green light laser when they were rotating the fiber they made a very I'd say standard rotation movement very they didn't adopt the rotation
- speed or the distance of the fiber to the issue to the moment in the operation on here you have to be constantly playing with the fiber distance on the let's say angle of incidence where where do you where do you fire if you fire against the line of attack or closer to the adenoma you know you have to play with this tissue effects targeting practice to get exactly what you want you have to change your strategy during the operation so it doesn't it's very concentrated let's say activity where you have to be absolutely focused on what you're doing again stay close to the another well I feel there let's say
- the weight of the Anoma on my scope which means that I need to push a little bit upwards if I want to go in that plane so what I'm going to check now is where is the UO in relation to where we are now let's see where it is it was close here so why because I want to cut here in the gladder neck towards the midline a little bit so I can let's say rotates the enema and push it into the bladder even when there is some remaining attachment at 6 o clock so here I'm liberating a little bit in the lateral aspect careful movements but as I gets
- here near the UO and see we have to be careful I will cut more into this edge sometimes we are very very close to the host but this way also what I'm doing is I'm making the hinge the pbot of the rotation of the adenomas are very very narrow you need to rotate the Noma with this bladder next in a touched here it's going to be very difficult but if you make it narrow then it's going to be much easier oh that's the UO there and seats it's very very very close so I'm going to be
- very careful here just as we did on the other side just try to say release a little bit naturally here let's say from lateral to medial
- and again that's it now we can cut here I think here it's safe and again we are making the hinge very thin in the midline so now I'm going to try to do it most asses because see while we maintain a nice laminar flow in this space you know because we can see the capsule we can have good disability and we can carry on our demos classes actually push the Nova in the ladder then the flow inside the portal is very chaotic which means that there will be blood everywhere we cannot flush it so easily so it's
- nice before turning the the tipping how do you say tipping the Nama into the ladder flipping it you can do your Hema status here you see it's quite capsular we found a leading [Music] bumper here somewhere
- maybe I ran out of water that's the reason as well for more disabilities hear this so it's very nice to know that how most assets while they are normally seen in the fossa because you see we get much better disability and even when we get good hemostasis inside the posture when we push their Norma into the bladder you can see that the visibility drops a little bit you know never looks the same I think some planes are more inflammatory some planes are a little bit less inflammatory sometimes we see a
- beautiful let's say interface between the normal on the capsule
- here I wouldn't go inside because below I mean behind this there's the you uh-huh just to do some homeostasis of this area get the vessels okay somewhat better let's see the posterior aspect sometimes we don't pay too much attention to this senior aspect but sometimes there are some leaders here as well
- you see I'm playing with the distance because this is the same setting that 250 I'm playing with a distance to get a probability of effect that it's not aggressive no sometimes when you have a very flimsy very thin capsule by trying to correlate if you get too close you can cut open no the plane or the capsule so you have to you have to get very very good sensitivity and develop this sensitivity so you can tailor the laser effect on the tissue depending on the clinical scenario this is I'd say more bloody than usual this patient I don't know why though we've done other cases
- and we didn't see this kind of hyper vascularity it's starting to look better and better this the penetration of these energy is very shallow it's not not dangerous to use this energy in the prostate he penetrates very very not ready these are the bleeders you want to get the ones that are pouring blood into the party
- fields okay see what happens if we lift see I'm going to put my scope under the lobe try to lift it a little bit see what's happening so
- mechanically you can do some harm as well so to be careful I wanted to leave the normal to see if I could push it into the bladder but now I have a better view of the attachment at 6 o'clock let's lift the other side as well see no now what I achieved is to push the Nama in the bladder all right look how the visibility follows up in inside the fossa see much worse could be an anomaly who's going retro trigonal here's the bladder neck they all must be near here somewhere
- there is a it's safe but closer and this is the attachment here last attachment you see sometimes it's difficult to get there from from below so if you tilt the Nama in the latter becomes much easier to target it this one of the things that are not so nice from the whole game is that this explosive nature of the home Ian when you get to the mimosa sometimes it generates a little bit of bleeding so these mu partial vessels tend to tend to
- bleed a little bit and see you all again all right safe but close as well you have to insist a little bit to new hostess is what we finished it's probably to cut longer than usual this separation was a little bit bigger prostate but more because of the bleeding tendency I don't know why you see there's some bleeding still let's see if there's any big vessel that is contributing to this some of these vessels sometimes when you populate them improve
- significantly it's true that we didn't concentrate on the interior prostate and they're known before it's a tilting their number
- well you have you have to try to get good kind of status before more station and if you can't then you go in with a rollerball look at the this is normal growing retro secondly you see so out entering the capsule just by keeping close to the adenoma huh if you don't get good feasibility - too much late then what you have to do is you you have to go in with a rollerball and try to make it perfect or make it better some oozing still
- okay I think it's probably good enough see if we find any [Music] well here this it's my Farah and this not much much closer and very frightening but no but you have to be careful for a little bit more or less more too late I'm going to take off the timer and see we can do a fast changing instruments without decompressing the
- bladder too much okay now the urine coming out of the it's quite clear it's not very bloody so I think we can progress to more sensational okay manga water in please that's a clot see those are close already it's just a clock and we are under the clot so you can you can suck suck the clot that's tissue so let's start the
- modulation again I like to go below the adenoma you know typically the the water that comes out during the change of instruments you fill it up again while getting ready to marshal it you know what I mean so I close the outflow I leave the inflow open and I try to keep the bladder more or less distended here I'm keeping the blade inside the bladder so I can see the an amount top and I can see the two corners around the blades you tell me that I am in the center of the bladder more or less this
- modulation with the peroneus system is amazing because it's pretty fast but also if you think about it you know I'm just still in the middle of the bladder and the tissue is coming to the blade so I don't need to move I don't need to fish very often so when more sedation is sufficient like this it's wonderful that I don't use the second inflow like most people do but I am very very careful of the balance between in water going in and what we got coming out if you cannot see the mouth of the modulator now we cannot see it this is the mouth we only see tissue in contact with it there will be very little amount of water coming
- out a lot of tissue if we can see the mouth a lot it means that you're sucking out a lot of water and then you have to be careful because the latter can empty and then a lot of wall comes closer to the modulation blades I have had accidents in the past but they were luckily not terrible accidents and it could be sorted conservatively but of course experience helps with modulation in the sense that you are more confident you can work let's say with a little bit worse visibility of course you shouldn't be overconfident I think there is a window of opportunity
- for modulation you know when you do your homeostasis and you have let's say good visibility you start your modulation and what you want to do is to want to finish as soon as possible because extending the bladder to more than 20 minutes is going to cost leading bleeding from the for style that gets distended again bleeding from the bladder from the mucosal edges you know and also because we are not let's say we don't have a continuous flow system we have entrance of water and there's some outflow but it's it's not an efficient washout so more and more the visibility is going to be great you cannot take the tissue out in 20 minutes it's very likely that you're going to
- need to stop change the instrument go in with a laser or the rollerball to coagulate further you know and then start again with modulation and then it becomes less less beautiful there's less efficient and sometimes pain not finishing these operations when when there's bad visibility also dangerous so that's why I recommend everybody to invest in a very good morcellator their number of them now in the market which give you very good motivation rates and the moment the perennial system is my my favorite the storts modulator has improved it was very slow at the beginning but I tried it recently and I have to say my opinion is probably
- a little bit slower than the perennial but is still fast and I have heard about this Chinese Morse later on the hawk modulator people who use it say that it's very fast so larger prostates take a little bit longer to Marshall eight but there's nothing we do differently in patients with larger four states as compared to this smaller ones we leave a catheter in the same way overnight we take it out in the next morning the same way we have a protocol to remove the catheter that's to wash the bladder before removing the catheter then deflate the balloon and withdraw the catheter a little bit so
- the tip of the catheter goes in the study for some and then wash the fossa to take clots out sometimes when you have retention possibly it's because they're clots in the form and then we give we put 250 300 mils in the bladder as much as the patient let's say tolerate and after that we remove the catheter so the first mode is the immediate most of the times and the patient gets confident and he can pee and then we give him some for some eat or go 20 20 milligrams of personally I be they instruct them to drink plenty so in two or three hours they appear three
- times or four times sometimes one liter and we asked them to pee on a jar so we can see the color and the quantity if they pass reasonable coloration it's a red wine at the beginning then it becomes more like rosy wine then they can go home I tell this to my patients so they anticipate what's going to happen in the post-operative period because otherwise they can be very scared when they see the color of the urine when they pee many times they wash out is totally clear even a drop by drop wash out but when you when we take a bath crowd they have the material and in two occasions I had to staple a head wound in a patient who got
- fainted after seeing the red your in coming out so ya know it's a relatively large London it's taking quite a while to mostly I guess you're going to get a lot of tissue out but the Malaysian is very efficient and very happy also for us it was very important to find this five liter containers for the most nation device because instead of having to change the container one or two times during MRSA nation we managed to to marshal a most of the times in one go without so typically the device comes
- with a three liter container but Mandela the company is producing five meter which works equally well the back home takes a little longer to establish of course but it's very very very nice to be able to modulate large amounts of tissue without stopping us as we had to do before it's important to as a surgeon to know how to use the modulator and all its subdued seventies you know because if you're going to buy a modulator make sure that the company tells you everything about the device what could go around what could happen because when when you are in this moment in the operation where matter is extended visibility is falling slowly you don't want to spend a lot of time trying to
- pinpoint what's going on with the modulator wide that's an oscillation work you know so maybe the bucket of tissue is quite full now and that can sometimes compromise the sucking it's a force negative pressure so this action is a little bit milder you see and sometimes you lose the so every time you changed the forceps you know it's important to also change the tissue basket because the tissue tends to firmness it because in this section the section has to go through the tissue basket you know negative
- pressure is transmitted to the tissue basket so the I'm going to try to bring it into the fossa let's see now we are in the fossa but still not good now you see visibility is dropping a little bit so there's still one piece if I can find it it went into the foster this is a small clot forming just it again but I'm going to go in with our sector scope to check me I'm going to check with our sector scope to do the final check sometimes it's necessary you know for example with
- the motorists we don't need to issue me there's only a mild mild hysteria coming out in the moment we put the catheter is going to be okay but I want to check I want to check that there's no definite / / - oh right yes okay see you into color
- so there we are let's have a look listed this is a monopole very successful you don't have a bipolar because we we don't do to you RP that's an empty bladder see there is some oozing uooo uooo again it's the for solid see if there's any piece inside doesn't look as if there is any piece and then look at this thing - you see we managed to preserve them of course are on the sphincter there's a little bit of damage I think going in probably those of these cops follow us you see this small clot forming but it
- doesn't seem to be any let's say residual oh yeah there's a small piece you need to try - it's not it's not well connected it's a piece thing is the one that we try to lure into the fossa before but of course the visibility in the fossa was not so good so we lost it where is it Thomas some problem with the electric car no I think we can pull it out let's try see
- if I can cut on the on the piece okay no no I mean conectado it's gonna tell Ariana I say connect ow are you okay okay now this is cutting as it's monopolar it will only cut when it's in contact with the capsule you know the the current has to go through the adenoma and then into the capsule of the prostate and then out through the electrode in the skin so now I'm bringing the piece out through the the
- artists that's it when we have finished I'm going to make a last look let's look again a good sphincter good cavity I don't see any major bleeding it's like more losing no look if you look at this let's say capsule that looked very frightening at the end there while we were doing the laser you can see that there is a tissue layer there you see Molly actually finishing in the moment you see it looks very frightening with the laser but when you go in with our sector scope is not so frightening it looks you can see
- I think the balloon will stop this siga yeah nothing major yeah once it's coming out basically very clear I think also you know that I don't see any bleeder active leader so it's more like losing from there when we when we stop live this tension all of this is going to contract I thing and losing will stop but there's no dishonor in going in and check for example this result would be a problem huh you know what I mean it's it's a it's patient safety what you want so you want
- to go in and finish the procedure by checking the hem of star system you can do yeah but you know there are no my grouse on the on the Trigon and beagle behind the Trigon and you know this patient what time is it now it's 7:00 and 8:00 p.m. tomorrow morning at 8:30 something like that the catheter will come out you will go home and I don't think you can do a TRP that is so anatomic all right
- you finished so it's been a pleasure to to having you here this is your home you can come anytime any